Sirolimus-Coated Balloon Beats Plain Angioplasty in First US Randomized Trial
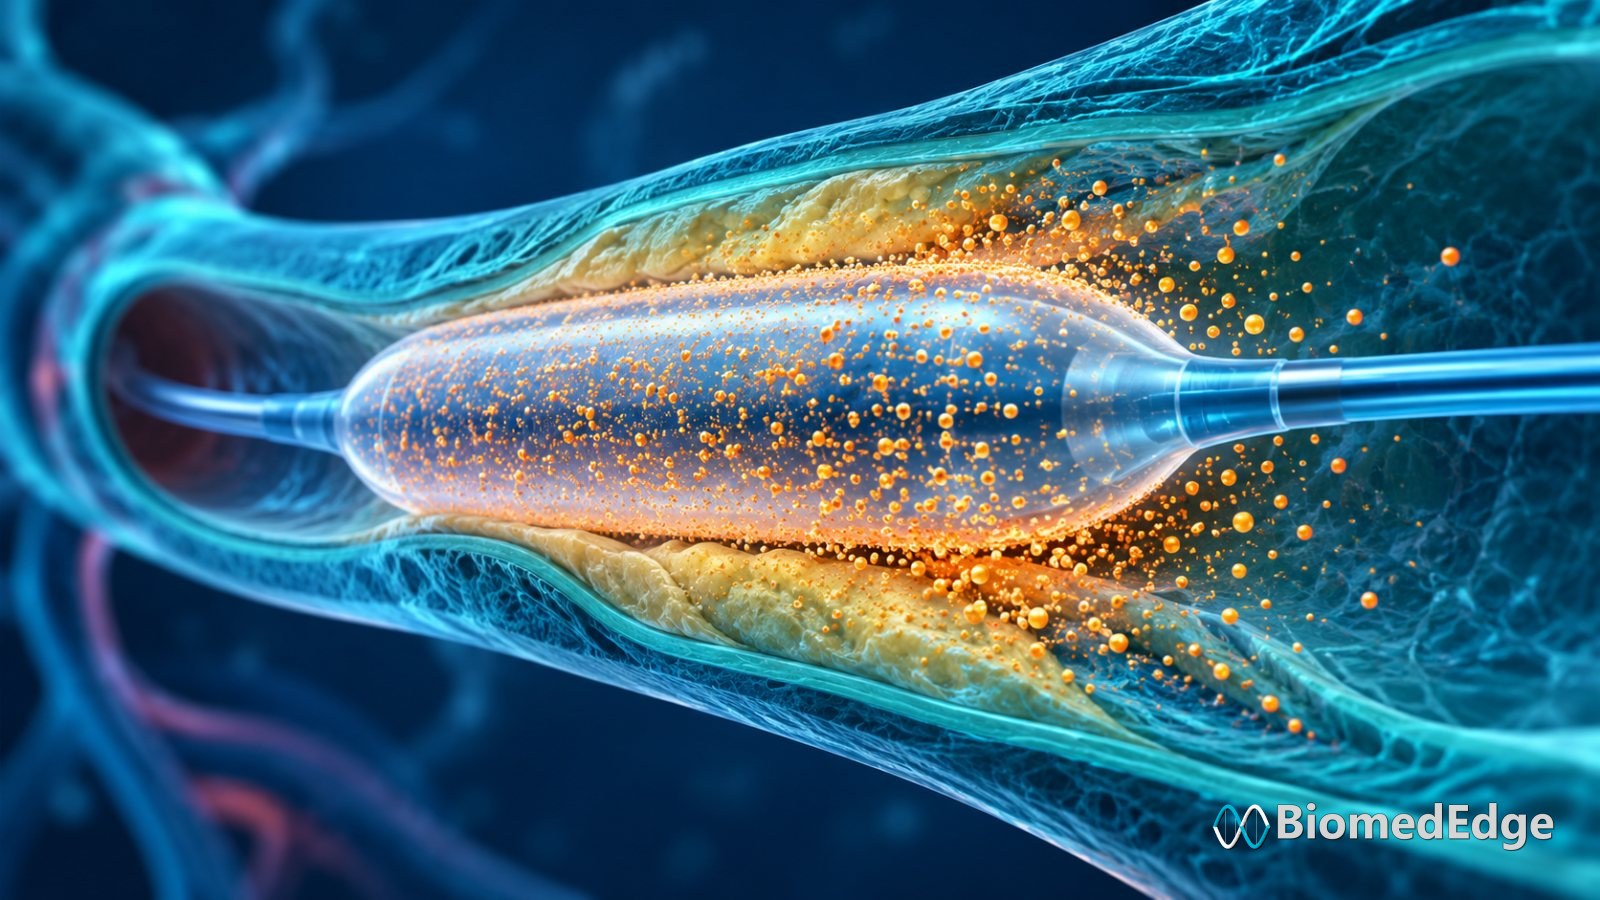
SELUTION4SFA randomized 300 patients with narrowed leg arteries and met both its efficacy and safety endpoints, offering the field an alternative to paclitaxel.
At the VIVA meeting in Las Vegas in early October 2026, investigators reported the first results of SELUTION4SFA, the first US randomized trial of a sirolimus-coated balloon for peripheral artery disease. The device beat plain balloon angioplasty on its primary efficacy endpoint, and the trial supports a pending FDA submission by its sponsor, Cordis.
The result matters beyond one device. For more than a decade, drug-coated balloons in the leg have meant paclitaxel. A safety controversy that has since been partly resolved, and a European guideline that has moved on anyway, have left the field looking for an alternative drug. SELUTION4SFA is the first US randomized evidence that one works.
The problem with opening a leg artery
Peripheral artery disease narrows the arteries supplying the legs, most commonly the superficial femoral artery in the thigh. Patients develop pain on walking, and in advanced disease, rest pain and tissue loss. The standard minimally invasive treatment is balloon angioplasty: a catheter is threaded to the narrowing and a balloon inflated to crack and compress the plaque and widen the channel.
The difficulty is what happens next. Stretching an artery injures it, and the vessel responds by proliferating smooth muscle cells in the wall. Over months this neointimal growth can re-narrow the segment, a process called restenosis. The femoropopliteal segment is a particularly hostile site, because the artery is long, bends with the knee and is subject to compression and twisting.
How a drug-coated balloon works
A drug-coated balloon tries to interrupt that healing response without leaving hardware behind. The balloon carries an antiproliferative drug on its surface. During the brief inflation, typically a couple of minutes, the drug transfers into the arterial wall, where it suppresses the cell proliferation that would otherwise cause restenosis. The balloon is then deflated and removed. Nothing is implanted, which keeps future treatment options open, an advantage over a permanent stent in a vessel that moves as much as this one.

The engineering problem is holding on to the drug long enough to deliver it. Most of the coating must survive the journey through the vasculature, then release into the wall during a short inflation, then persist in the tissue for weeks. The Selution SLR device approaches this with sirolimus mixed into a biodegradable PLGA polymer to form micro-reservoirs roughly four micrometres across, held on the balloon by an adhesion technology and protected by a phospholipid blend intended to reduce wash-off during delivery. The reservoirs degrade gradually, releasing drug over a period the manufacturer puts at up to 90 days, at a dose of about 1 microgram per square millimetre.
Why sirolimus rather than paclitaxel
The two drugs work differently. Paclitaxel stabilizes microtubules and is cytotoxic: it kills dividing cells. Sirolimus inhibits mTOR and is cytostatic: it arrests the cell cycle without killing. In principle the second approach offers a wider margin between an effective and a toxic dose, though that has been easier to assert than to prove.
The practical history is more complicated. In December 2018, a meta-analysis published in the Journal of the American Heart Association reported higher late mortality among patients treated with paclitaxel-coated devices in the leg. In August 2019 the FDA warned that these devices were potentially associated with increased mortality and asked for label changes. Then, in a letter dated July 11, 2023, the agency reversed course: a fuller analysis conducted with manufacturers did not support an excess mortality risk, and the warning was withdrawn. The FDA still advises routine monitoring and discussion of options.
European practice has nonetheless moved. Clinicians at the meeting noted that the Swedish SWEDEPAD trial renewed safety questions, that a European Society for Vascular Surgery guideline update in June 2026 says paclitaxel may be considered only for selected cases of restenosis, and that paclitaxel devices have become hard to source in Europe. A sirolimus option is therefore wanted whether or not the original signal was real.
The trial
SELUTION4SFA was a prospective, multicentre, single-blinded randomized trial at 34 sites across the US, Europe and Asia. Three hundred patients with symptomatic disease of the superficial femoral or proximal popliteal artery were randomized 2:1, with 205 receiving the sirolimus-coated balloon and 95 plain balloon angioplasty. Mean age was about 70 in both arms, and roughly 40% of patients had diabetes.
Worth noting: lesions in the device arm were longer, a mean of 9.3 cm versus 7.2 cm (P = 0.002), and about half of patients in each arm had severe calcification. The treated group therefore faced somewhat harder anatomy.
Results at 12 months
- Primary efficacy endpoint (superiority): primary patency of the target lesion at 12 months, 78.6% with the drug-coated balloon versus 65.2% with plain angioplasty (P = 0.019). Met.
- Primary safety endpoint (non-inferiority): a composite of freedom from perioperative death at 30 days plus freedom from target limb amputation and clinically driven target lesion revascularization at 12 months, 92.8% versus 84.2% (P < 0.0001). Met.
- Kaplan-Meier primary patency: 90.3% versus 79.4% (P = 0.006).
- Kaplan-Meier freedom from clinically driven revascularization: 94.6% versus 85.3% (P = 0.006).

The presenter, Jay Mathews of Manatee Memorial Hospital, described the Kaplan-Meier patency figure as among the highest one-year rates reported in a US drug-coated balloon pivotal trial. He also made a point about the comparator that cuts against his own result: plain balloon angioplasty is often criticised as a weak control, but technique has improved, which makes the control arm tougher competition than in older trials.
Supporting data from the same meeting
Two other sirolimus datasets were presented. A secondary analysis of the randomized SirPAD trial, restricted to 421 patients without tissue loss, reported target lesion revascularization in 17.0% with a sirolimus balloon versus 27.1% with an uncoated balloon, and major adverse limb events in 4.1% versus 8.9%. Separately, the SUCCESS PTA registry of 720 patients treated in Europe, Asia and South America reported freedom from revascularization of 86.1% at 24 months, and 83.0% among those with chronic limb-threatening ischaemia. The registry has no comparator arm.
Limitations
- The comparator is plain angioplasty, not paclitaxel. The trial shows the device beats doing nothing pharmacological. It does not show it is better than, or as good as, the paclitaxel balloons it would replace.
- Twelve months is short for a disease defined by late restenosis. One observation at the meeting was that paclitaxel devices typically lose about ten percentage points of patency a year, and whether sirolimus follows the same curve is unresolved.
- Baseline imbalance. Lesion length differed significantly between arms, in the direction that disadvantaged the device, but imbalance in a randomized trial still complicates interpretation.
- Single-blinded and industry-sponsored, as are the supporting studies; SirPAD was funded by the manufacturer of the balloon it tested.
- Not yet available. The device remains investigational in the US and is not commercially available there.
What to watch
- The FDA's decision on the Cordis submission, and what indication any approval carries.
- Two- and three-year follow-up, which will show whether the patency advantage holds or decays.
- Head-to-head trials of sirolimus against paclitaxel balloons, the comparison clinicians actually need.
- Subgroup analyses by calcification and vessel preparation strategy, which the presenter flagged as the open question.
- Whether sirolimus devices perform below the knee, where limb salvage rather than patency is the goal.
This article is for information only and is not medical advice. Treatment decisions should be made with a qualified clinician.
Sources: VIVA Foundation late-breaking results; TCTMD; Endovascular Today; Vascular News (FDA paclitaxel update); ClinicalTrials.gov NCT05132361
What did you think of this article?
Found this helpful? Share it!
Comments (0)
Leave a Comment
Be the first to comment!