When the Standard of Care Moves: What CARDIO-TTRansform Reveals About Trial Design
Eplontersen missed its primary endpoint in 1,432 patients with amyloid cardiomyopathy, yet slowed functional decline. The explanation lies in what patients were already taking.
At the Heart Failure Society of America meeting in Phoenix in October 2026, investigators presented the quality-of-life and functional results from CARDIO-TTRansform, the largest randomized trial ever run in transthyretin amyloid cardiomyopathy. The drug, eplontersen, had already missed the trial's primary endpoint. The functional data showed patients on the drug declining more slowly than those on placebo.
That combination makes CARDIO-TTRansform one of the more instructive trials of the year. It enrolled 1,432 patients, suppressed its target protein as intended, and still failed to show a reduction in cardiovascular death and events. The reasons appear to have less to do with the drug than with how much the treatment landscape shifted while the trial was running.
The disease
Transthyretin (TTR) is a protein made mainly by the liver. It normally circulates as a four-part complex, a tetramer. In transthyretin amyloidosis, tetramers come apart into single units that misfold and clump into amyloid fibrils. When those fibrils deposit in heart muscle, the walls thicken and stiffen, the conduction system becomes infiltrated, and patients develop progressive heart failure and arrhythmias. Before disease-modifying treatment existed, median survival was two to six years.
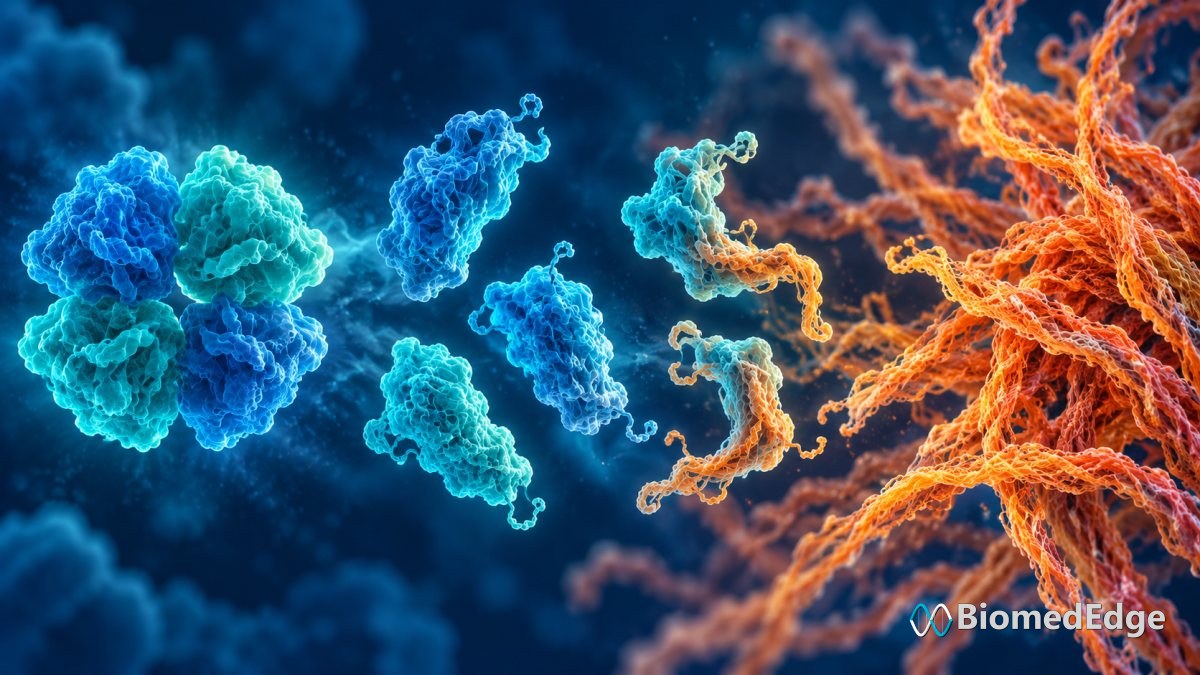
Two drug strategies follow from that biology. Stabilizers, such as tafamidis and acoramidis, bind the tetramer and hold it together so it cannot dissociate. Gene silencers, such as vutrisiran and eplontersen, cut production of the protein at source in the liver. Eplontersen is an antisense oligonucleotide given by subcutaneous injection every four weeks. It is a short synthetic strand of nucleic acid designed to pair with the messenger RNA that carries the TTR instructions, marking it for destruction before the protein is ever made. The result is less TTR in the bloodstream and, in principle, less raw material for new amyloid deposits. The approach had already been shown to slow the nerve damage caused by the hereditary form of the disease, which is what made the cardiac trial worth running.
The trial
CARDIO-TTRansform randomized 1,432 patients 1:1 to eplontersen 45 mg or placebo every four weeks for up to 140 weeks, across 130 centres in 20 countries. The population was typical of the disease: mean age 76.4 years and 90.6% men. The primary endpoint was a composite of cardiovascular mortality and recurrent cardiovascular events.
Eplontersen did what it was designed to do biologically, lowering circulating TTR substantially. But the primary endpoint was not met: the rate ratio was 0.89 (95% CI, 0.73 to 1.09; P = 0.277). Cardiovascular deaths were 74 on eplontersen and 70 on placebo. The full results were published in the New England Journal of Medicine in August 2026.
The functional endpoints presented at HFSA by Brett Sperry of Saint Luke's Health System pointed the other way. Scores on the Kansas City Cardiomyopathy Questionnaire fell by 5.4 points on eplontersen versus 9.4 on placebo, a 4.0-point difference (P < 0.001). Six-minute walk distance fell by 27.5 metres versus 47.3 metres, a difference of 19.7 metres (P < 0.001). Patients on the drug felt and functioned better, but did not live longer or have fewer cardiovascular events overall.
Both of those measures are standard in heart failure research. The Kansas City Cardiomyopathy Questionnaire is a patient-reported instrument covering symptoms, physical and social limitation and quality of life, scored from 0 to 100, where a change of about five points is generally taken as clinically meaningful. The six-minute walk test records how far a patient can walk on a flat course in six minutes, and is a practical proxy for functional capacity. In a progressive disease, holding a score steady is itself a result, which is why both endpoints here are reported as a smaller decline rather than an improvement.
Why the trial may have missed
The most striking finding came from a prespecified analysis published in Nature Medicine. When the trial began, stabilizer therapy was not standard; by the time it finished, it was. Of the 1,432 patients, 819 (57.2%) were already taking a TTR stabilizer at baseline, all of them tafamidis.
Baseline stabilizer use turned out to modify the treatment effect, with a statistically significant interaction (P = 0.017):
- Patients not on a stabilizer at baseline (n = 613): 172 primary endpoint events on eplontersen versus 221 on placebo, a rate ratio of 0.71 (95% CI, 0.54 to 0.93; P = 0.012). Six-minute walk distance was better by 29.9 metres and KCCQ score by 7.6 points, both P < 0.001.
- Patients already on a stabilizer: rate ratio 1.14 (95% CI, 0.85 to 1.53; P = 0.39), with no added benefit.
The interaction was consistent for recurrent cardiovascular events (P = 0.009), KCCQ score (P = 0.002) and NT-proBNP (P = 0.003), though not for six-minute walk distance (P = 0.085), cardiovascular mortality (P = 0.74) or all-cause mortality (P = 0.44).

There is a plausible mechanism. If a stabilizer is already preventing tetramers from dissociating, further reducing how much TTR is produced may add little. Both approaches converge on the same step in the disease.
The design issue compounds it. Stabilizer use was unrestricted throughout the trial, and among patients who began without one, 57.0% in the eplontersen arm and 56.5% in the placebo arm started one during follow-up. So the "monotherapy" comparison was increasingly not monotherapy on either side, which if anything would dilute a real difference.
How much weight the subgroup can bear
This subgroup result is stronger than most, because it was prespecified, the interaction test was significant, and a mechanism explains it. It still has real limits.
- The trial was negative. A subgroup finding inside a trial that missed its primary endpoint is hypothesis-generating. It does not establish benefit.
- Mortality did not improve. Even in the no-stabilizer group, cardiovascular mortality (HR 0.93; 95% CI, 0.62 to 1.39) and all-cause mortality (HR 0.84; 95% CI, 0.60 to 1.18) were not significantly reduced. The benefit sat in non-fatal events.
- The groups were not alike. Patients on stabilizers at baseline were younger, had longer-known disease, better walk distance and KCCQ scores, lower NT-proBNP and less advanced disease stage. The two subgroups differed in prognosis, not only in treatment.
- Timing differed. Median time from diagnosis to enrolment was 0.5 years for patients not on stabilizers and 1.1 years for those on them, with a median of nine months of prior stabilizer therapy.
- Open-label crossover. More than half of the no-stabilizer group started a stabilizer during the trial, so the comparison is not clean in either direction.
Safety was not the problem. The trial reported a favorable safety profile for eplontersen regardless of baseline stabilizer use.
The broader lesson
CARDIO-TTRansform is a case study in a problem that affects any long outcome trial in a fast-moving field. The trial ran for up to 140 weeks against a background therapy that became standard partway through. A placebo arm in which most patients end up on an effective drug is no longer a true placebo arm, and the question the trial answers quietly changes from "does this drug work?" to "does this drug add anything to what people are already taking?"
It is also a reminder that a biomarker is not an outcome. Eplontersen lowered TTR substantially, which is exactly what an antisense drug should do, and that alone did not translate into fewer cardiovascular events in the trial population as a whole.
What to watch
- Whether regulators regard the prespecified monotherapy analysis as sufficient to support any labelled use, or require a confirmatory trial in stabilizer-naive patients.
- Trials designed explicitly around combination questions, testing silencer plus stabilizer against stabilizer alone.
- Results from other TTR silencers and from amyloid-depleting antibodies, which attack deposited fibrils rather than production.
- How future ATTR-CM trials handle background therapy, including stratification by stabilizer use at randomization.
- Whether the functional benefits seen here hold up as a treatment goal in their own right, given that patients value how they feel and function.
This article is for information only and is not medical advice. Treatment decisions should be made with a qualified clinician.
Sources: Nature Medicine (prespecified stabilizer analysis); HCPLive; AstraZeneca; ClinicalTrials.gov NCT04136171
What did you think of this article?
Found this helpful? Share it!
Comments (0)
Leave a Comment
Be the first to comment!